
Normally I don’t bother with preprints, particularly ones from Zenodo, but Hulscher is once again spreading his unsupported conclusions. Preprints are always suspicious which is why waiting for publication is usually best practice. Legitimate journals don’t publish garbage overall, although some things slip through the cracks that should never have seen the light of day. Zenodo is even worse, because anyone can upload about anything.
Once again, there are so many flaws in this that it’s misleading. First, the National Health Interview Survey (NHIS) is a cross-sectional study. One way to think of it is that it is a snapshot in time that counts exposures and outcomes. As such, it’s impossible to make any inference from dose (i.e., vaccination) and response (autism spectrum disorder, ASD), because there is no timeline, but this is exactly what they are doing. The NHIS doesn’t collect the data to make a study of autism risk possible.
For example, they claim “Associations for current ASD weakened with time since first dose.” Any decent peer reviewer would automatically throw this out for claims like these when they are IMPOSSIBLE to make using the design of the NHIS.
A second major flaw is that the NHIS is a survey that relies on parental reports, not medical diagnosis. This means that many of the children in the survey can easily be misclassified as having ASD when in reality they do not.
Another flaw is that children who get vaccinated are categorically different from those who don’t. They are likely to have better access to care, better insurance coverage, more educated parents, and more likely to be screened for things like ASD. The authors are completely misusing the NHIS to push their claims.
Another claim that would be caught by reviewers is small sample sizes. “for lifetime ASD, n =19,788 with 470, 44, 214, and 115 cases across 0, 1, 2, and ≥3 doses).” With numbers that small, the results are unstable and essentially meaningless. Those numbers get even smaller when broken down by age, which is absolutely essential for studying ASD. There is no way to say anything meaningful using the exposed cases from their own ASD table.
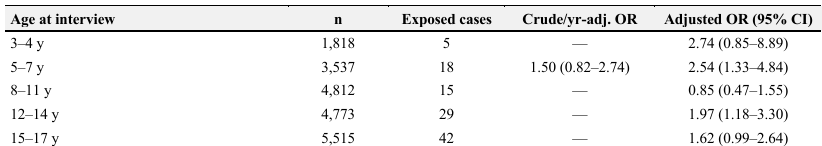
When a sample size is this small, one can make wild claims about the significance of a variable. For example, if I took 5 murderers and four of them wore glasses or contacts, I could make a claim that 80% of murders have vision problems. In addition, when they ran as many statistical tests as they did, they will find some correlations, because that is the nature of statistics. This is what is referred to as data mining and relies on cherry-picking data. If you run enough tests, you can always find something that looks “significant” even when nothing real is happening
Another major flaw is their use of what they claim are controls. Emergency department visits and hospitalizations are not accurate control groups when looking at developmental outcomes. Developmental issues cannot use acute illness as controls.
These authors are also prone to use speculation to support plausibility and often rely on animal studies, which is rather odd given that animals aren’t diagnosed with autism.
There are many other flaws, but this should be adequate to throw this paper out. One final point though is that when they have to use bad methodology to create their narrative, it’s a pretty safe bet that their adjusted odds ratio is suspect as well. In this case, it’s worth looking at the crude odds ratio.

This is the most damning piece of evidence of all. When the 95% CI (the confidence interval) includes the value of 1.0, that means that there is ZERO difference between groups. They haven’t proven anything other than that they consistently push a false narrative.

